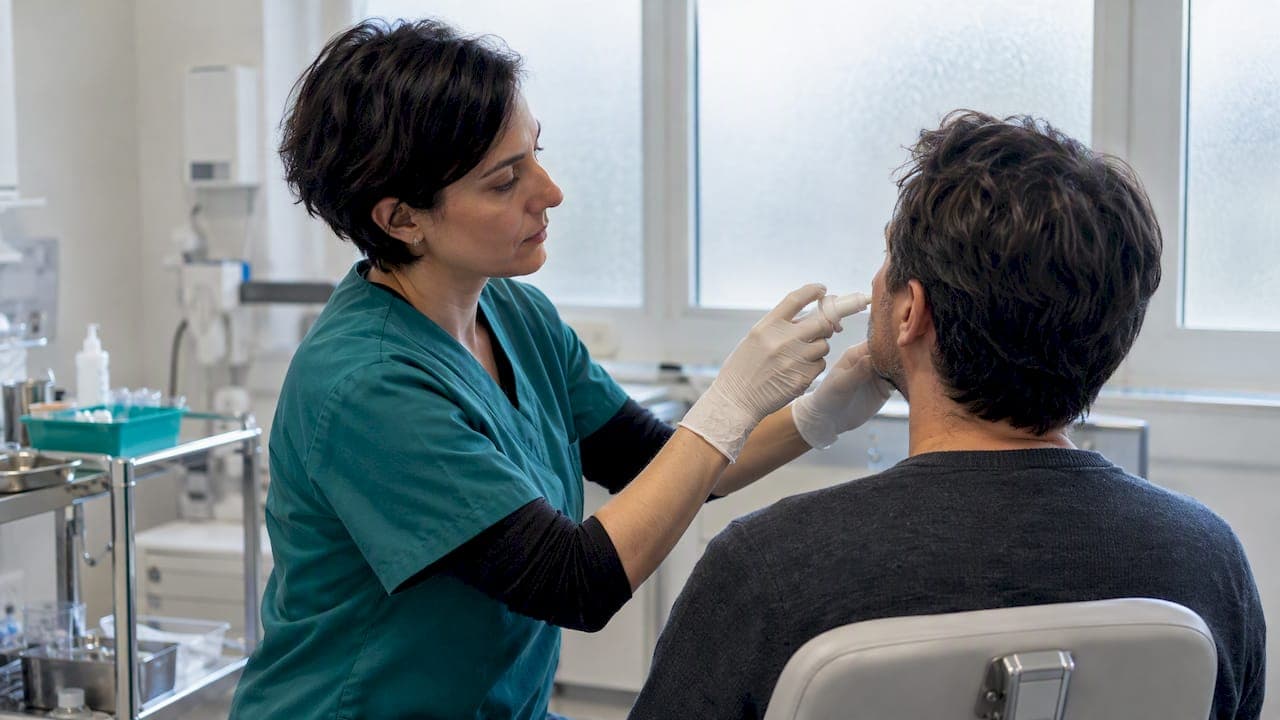
Intranasal peptides show peptide-specific, early human signals of brain pharmacology. That promise is conditional, not proven clinical benefit, and it depends heavily on formulation, device, and dose. Researchers working in this space must treat delivery hardware and regulatory context as part of the experimental design, not an afterthought. The sections below lay out the evidence, the mechanisms, and a reproducibility checklist for anyone designing a study.
TL;DR:
- Only intranasal insulin has shown consistent biomarker and imaging signals in human studies, with effects observed over 12 months but requiring larger trials to confirm efficacy.
- Variability in formulation and device design significantly influences how much peptide reaches the brain, emphasizing the need for standardized reporting and technique control in studies.
- Most peptides remain preclinical, and promising animal results have not yet translated into confirmed human clinical benefits across the broader intranasal peptide field.
- Proper measurement of nose-to-brain transport is challenging, with cerebrospinal fluid sampling and imaging providing more reliable data than blood tests alone.
- Regulatory standards demand that researchers match human safety and efficacy evidence to specific peptides, formulations, and routes before proceeding with intranasal peptide clinical studies.
Table of Contents
- Why researchers target the nose for brain-active peptides
- What the human trials on candidate peptides actually show
- Formulation and device choices that determine what actually reaches the nose
- How peptides move from nose to brain, and how to measure it properly
- Regulatory and ethical checklist before starting a study
- Building a reproducible study: protocol and sourcing checklist
- What still stands between promising signals and clinical translation
- Where the evidence leads and what researchers should prioritize next
- Sourcing research-grade peptides for intranasal studies
- Primary sources worth reading in full
- Sources
- FAQ
Why researchers target the nose for brain-active peptides
Peptides degrade fast in the gut and clear quickly once injected, which limits oral and systemic routes for anything meant to act on the brain. The nasal cavity offers a route that may bypass first-pass liver metabolism and, for some molecules, provide more direct access to the central nervous system through the olfactory and trigeminal pathways.
That rationale has driven intranasal peptide research across a range of neurological and psychiatric targets. The same review notes that intranasal delivery is being studied as a strategy to avoid gastrointestinal degradation, not as a confirmed shortcut to the brain.
Clinical areas currently drawing research interest include:
- Alzheimer's disease and mild cognitive impairment, where insulin signaling and amyloid clearance are study targets.
- Parkinson's disease, where dopaminergic and neurotrophic peptide effects are under investigation.
- Depression, PTSD, and social cognition research involving oxytocin.
- Narcolepsy and sleep-wake regulation, an area associated with orexin-pathway peptide research.
- Chronic pain, where peptide analgesics are being tested as alternatives to systemic opioids.
Oral peptides face enzymatic breakdown before absorption, and injectable routes carry compliance and access burdens for repeated dosing. Intranasal administration is attractive because it is noninvasive and allows repeated self-administration in a trial setting, though none of that guarantees that a given peptide reaches its intended target in sufficient concentration.
What the human trials on candidate peptides actually show
A handful of peptides account for most of the human-relevant data. The rest remain in preclinical stages, where promising animal results have not yet been replicated in people.
Intranasal insulin has the deepest human trial history. A 12-month study using 20 IU twice daily reported reduced progression of white matter hyperintensities alongside associated improvements in cognition and cerebrospinal fluid biomarker profiles in older adults with mild cognitive impairment or Alzheimer's disease. A more recent randomized phase 2A/B trial tested 40 IU four times daily for 4 weeks in a 2x2 factorial design combining insulin with empagliflozin, in people with MCI, early Alzheimer's, or amyloid positivity. Adverse events were mild, and cognitive and biomarker signals were promising, but the trial authors called for longer and larger studies before drawing conclusions about efficacy.
Semax, a synthetic ACTH-fragment peptide, has a long history of intranasal human research use, primarily in contexts outside large Western regulatory trials. Evidence for cognitive or neuroprotective effects remains far less rigorously documented in peer-reviewed randomized trials than the insulin data above.
Other candidates remain largely preclinical. NAP (davunetide) has shown neuroprotective signals in animal models and early-phase human studies but has not produced confirmed clinical efficacy at scale. GLP-1 receptor agonists delivered intranasally are an active research area building on their systemic metabolic and neuroprotective profile, but nose-to-brain human data are limited. Oxytocin has a substantial intranasal human research base in social cognition and psychiatric contexts, though dosing and outcome measures vary widely between studies. PACAP and NPY remain largely confined to preclinical models.
Reviews of this evidence base are consistent on one point: biomarker and pharmacodynamic changes are not the same as confirmed clinical benefit.
One 2022 systematic review of intranasal peptide therapeutics concludes that efficacy is peptide- and formulation-specific, with translational barriers including low peptide stability and enzymatic degradation still unresolved across the class. A useful outside primer on separating evidence from hype in peptide therapy makes a similar point for a broader audience.
Formulation and device choices that determine what actually reaches the nose
The formulation is part of the intervention, not packaging around it. Two studies using the same peptide but different sprays, particle sizes, or viscosities can produce different exposure profiles and different results.
Four delivery formats dominate current research:
- Liquid sprays and drops remain the most common format in human trials because they are simple to standardize and compare across dose arms.
- Dry-powder inhalers can improve peptide stability during storage and may extend nasal residence time compared to liquid formulations.
- Mucoadhesive gels slow mucociliary clearance, increasing the time a peptide sits in contact with nasal epithelium.
- Nanoparticle and liposomal carriers are under investigation to protect peptides from enzymatic degradation and to target specific nasal regions.
Permeation enhancers add another layer of complexity. Coadministration with cell-penetrating peptides such as L-penetratin has been shown in mechanistic preclinical studies to increase brain and hippocampal accumulation of insulin and exendin-4 in animal models, while also increasing systemic absorption. More brain delivery is not automatically safer or more selective, a point reviews of intranasal peptide therapeutics make explicitly.
Device and technique matter as much as the formulation itself. Targeting the upper nasal cavity and olfactory region requires different head positioning and spray mechanics than a standard decongestant-style nasal spray, and studies that fail to control for this introduce variability that has nothing to do with the peptide being tested.

Pro Tip: Report device model, administration volume per nostril, head position, and time between puffs or drops in the methods section; deposition differences from technique alone can account for divergent results across otherwise similar studies.
How peptides move from nose to brain, and how to measure it properly
Three pathways are usually invoked to explain nose-to-brain transport: the olfactory nerve pathway, the trigeminal nerve pathway, and distribution through cerebrospinal fluid, perivascular, and glymphatic spaces. Evidence for these routes is strongest in preclinical models and considerably weaker and harder to confirm directly in humans, partly because humans have proportionally less olfactory epithelium than rodents, which complicates translation of encouraging animal data.
This is why measurement design matters as much as the peptide itself:
- Plasma sampling alone cannot distinguish systemic absorption from direct nose-to-brain delivery, since a peptide detected in blood may never have reached the brain through a nasal-specific route.
- Paired cerebrospinal fluid sampling, where ethically and practically feasible, provides a more direct readout of central exposure.
- Imaging endpoints, including structural MRI measures like white matter hyperintensity progression, add a clinically meaningful layer beyond biochemical markers alone.
- Biomarker panels such as CSF cytokines, amyloid, and tau proteins should be timed to known pharmacokinetic windows rather than collected on convenience schedules.
Reviews of the evidence base recommend correlating any biomarker shift with a cognitive or clinical outcome before treating it as meaningful, a discipline that separates pharmacodynamic signal from noise.
Regulatory and ethical checklist before starting a study
Unapproved peptide products sit in a specific regulatory category that researchers cannot treat as equivalent to approved medicines. The Therapeutic Goods Administration states plainly that unapproved peptide products have not been assessed for safety, quality, or effectiveness, and that any application for use must be supported by human evidence specific to the exact peptide, dosage form, route, and indication being studied.
Before initiating intranasal peptide research, address these points:
- Confirm the evidence match: human data supporting a peptide's safety or effect must align with the specific formulation and route planned, not a related peptide or a different administration method.
- Secure informed consent that clearly states the product is unapproved and that intranasal delivery for the studied indication remains investigational.
- Verify product quality through independent testing rather than relying on supplier claims alone.
- Confirm GMP and compounding compliance, since compounding guidance has recently tightened around some peptide classes, including restrictions on compounding GLP-1 receptor agonist analogues.
- Obtain institutional ethics and governance approval before any human-subject work begins, and consult the TGA early rather than after protocol finalization.
A dedicated overview of Australian peptide prescription requirements covers this regulatory landscape in more depth for researchers planning local studies.
Building a reproducible study: protocol and sourcing checklist
Reproducibility failures in this field often trace back to under-specified methods rather than flawed hypotheses. A tight protocol addresses each of the following before enrollment begins:
- State a specific hypothesis tied to one peptide, one formulation, and one measurable endpoint, rather than a broad claim about "nasal peptides" as a category.
- Randomize and blind wherever feasible, and justify sample size against the effect size seen in prior trials such as the insulin studies referenced above.
- Select endpoints in advance, whether cognitive testing, CSF biomarkers, or imaging measures, and avoid post-hoc endpoint selection.
- Reference prior human dosing rather than extrapolating animal doses directly; a dose that produced strong effects in rodents often requires substantial revision for human trials.
- Document peptide quality: HPLC purity above 99%, Certificate of Analysis, and batch-specific documentation reduce a major source of unexplained variability between labs. Researchers can use independently tested peptides with Certificates of Analysis available on request as supporting documentation in ethics or procurement submissions.
- Plan storage and handling for peptide stability, since degraded stock introduces dosing error that is easy to misattribute to biological variability.
- Schedule PK/PD sampling at pre-specified intervals, with adverse-event monitoring and reporting built into the protocol from the start.
Pro Tip: Keep a written formulation and device log for every study arm; small changes in spray mechanics between batches are a common, underreported source of failed replication. A practical resource on reproducible cognitive peptide research methods covers assay and documentation practices in more detail.
What still stands between promising signals and clinical translation
The biggest translational gap is anatomical. Rodent studies benefit from a much larger proportion of olfactory epithelium relative to total nasal surface area than humans have, so positive animal results require careful scaling and formulation revalidation before they mean anything in a human trial.
Several questions remain open: how selectively a given formulation targets brain tissue versus systemic circulation, what long-term safety looks like beyond the 4-week and 12-month windows seen in current insulin trials, which device and formulation pairings produce consistent dosing, and where the true dose-response curve sits for each candidate peptide.

The highest-value next trials are longer in duration, larger in sample size, paired with rigorous PK/PD sampling, and built around standardized device reporting, so results from different labs can actually be compared.
Where the evidence leads and what researchers should prioritize next
The conditional promise here is real but narrow: a small number of peptides, mainly intranasal insulin, have produced human biomarker and imaging signals worth pursuing further. Most of the rest of the field remains preclinical, and treating early signals as confirmed benefit does a disservice to the science.
Methods should come before molecules. Standardized device and formulation reporting would let separate research groups actually compare results, something the current literature struggles to do. Multi-center confirmatory trials, not single-site pilot studies, are what this field needs to move past conditional language.
Collaboration built on verified materials and full documentation removes at least one variable from an already complicated picture.
— Tintastic
Sourcing research-grade peptides for intranasal studies
Formulation variability is hard enough to control without adding peptide quality as another unknown.
For labs building ethics submissions or regulatory documentation, that batch-level traceability can support the evidence requirements outlined earlier. Bulk ordering is also available for trials requiring consistent supply across multiple dosing arms. Browse the research peptide catalogue to review available compounds and request documentation for a planned study.
Primary sources worth reading in full
For replication or deeper reading, start with the 2022 review of intranasal peptide therapeutics, the 2025 phase 2A/B insulin trial, the 12-month insulin biomarker study, the nasal aerosol delivery review, and TGA peptide guidance. A broader survey of emerging peptide research offers additional context on candidates outside the CNS space.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Intranasal peptide therapeutics: a promising avenue for overcoming the challenges of traditional CNS drug development
- Phase 2A/B trial of intranasal insulin (2025)
- Peptide product information for health practitioners — TGA
- Intranasal insulin reduces white matter hyperintensity progression in association with improvements in cognition and CSF biomarker profiles in MCI and Alzheimer's disease
FAQ
Do nasal spray peptides actually work?
Some do show measurable effects in early human trials, particularly intranasal insulin, which has been linked to reduced white matter hyperintensity progression and improved cognition and biomarker profiles over 12 months. Effects are peptide- and formulation-specific, and reviews of the evidence caution against treating this as proof across the whole category.
What vitamin slashes dementia risk by 40 percent?
This article did not find a vitamin study supporting that specific figure, and no source referenced here makes that claim. Readers interested in dementia risk factors should consult a primary clinical source rather than relying on a single statistic circulating online.
What did Bill Gates find out about Alzheimer's disease?
No source used in this research covers a specific finding attributed to Bill Gates regarding Alzheimer's disease. This question falls outside the scope of the intranasal peptide research this article addresses.
How many people died in the Donanemab trial?
This article's sources do not cover Donanemab trial mortality data, since the focus here is intranasal peptide delivery research rather than monoclonal antibody trials. Readers should consult the trial's original publication or regulatory filing for that specific safety information.
What is the biggest barrier to intranasal peptide research right now?
Enzymatic degradation and mucociliary clearance in the nasal cavity limit how much peptide actually reaches its target, and formulation choices like mucoadhesive gels or permeation enhancers such as L-penetratin are active attempts to address this. Human trials remain small and short relative to the chronic conditions being studied, which is why reviews of the field call for longer, larger confirmatory studies.